



There’s a man from California who has said close to 2 million words in the last couple of years without moving his lips.
His name is Casey Harrell. He has ALS; he can’t speak in a way people can understand. And he communicates through a set of electrodes sitting in his brain. Over nearly two years at home, he has produced more than 183,000 sentences at an average of 56 words per minute.
This is something I want to walk you through. Brain-computer interfaces, or BCIs, are systems that read electrical activity in the brain and turn it into an action.
Key Takeaways
- Harrell used his BCI for over 3,800 hours of independent, near-daily home use across almost two years.
- The system hit over 99% word accuracy in controlled testing with a 125,000-word vocabulary, up from 97% in the team’s earlier work.
- The number of people with brain implants has more than doubled since 2023, to roughly 150 worldwide.
- In 2026, China became the first country to approve a BCI for medical use outside of clinical trials.
- BCIs are still experimental, and nobody fully knows how long the implants keep working.
What Is a Brain-Computer Interface? Neurotechnology Explained
A brain-computer interface is a system that records brain activity and translates it into a command for a computer or device, without needing your muscles.

BCIs are one branch of a wider field called neurotechnology. It covers any tool that reads from or writes to the nervous system. Like deep brain stimulation for Parkinson’s is neurotechnology. And so is a research EEG cap. But what makes a brain-computer interface specific is the loop. Your brain produces a signal, software decodes what you meant, and something happens on a screen.
Every BCI runs the same three stages:
- Signal capture: The sensors pick up electrical activity, either from inside the brain or from the surface of the scalp.
- Decoding: A software translates those raw signals into intent, like a phoneme, a letter, or a cursor direction.
- Output: The decoded intent becomes an action: synthesized speech, typed text, a moved cursor.
The differences between BCIs come down to where they sit and what they do. Here’s the quick map:
| Type | Where it sits | Signal quality | Trade-off |
| Intracortical | Inside the brain tissue | Highest | Needs brain surgery |
| Surface (ECoG) | On the brain’s surface | High | Still invasive, less deep |
| Scalp (EEG) | Outside the skull, on the head | Lower | Non-surgical, noisier |
How Brain-Computer Interfaces Decode and Translate Brain Signals
So how does a brain-computer interface actually turn a thought into a spoken word?
It splits it into two jobs; reading the biology, and building the hardware that can hear it. Both matter, and they’re genuinely different problems.
The Neuroscience of decoding speech
Here’s the wildest part. When Harrell tries to speak, neurons fire in his precentral gyrus, a strip of cortex that coordinates with the mouth, tongue, and vocal movements. Even though the paralysis stops his muscles from following through, but the neurons still fire the instructions. A speech BCI reads those instructions.

The software doesn’t decode the words directly. It decodes the phonemes. It’s the small units of sound that make up the speech and then predicts the most likely word you’re building. Harrell’s system worked across a 125,000-word vocabulary, hitting over 99% accuracy in controlled testing, up from 97% in the team’s earlier work. That’s close to the full range of everyday English, rather, and the jump from 97% to 99% is a difference between a system you trust and the one you keep correcting.
This is also where speech decoding parts ways with movement decoding. A movement BCI reads intended arm or cursor motion, which is a smaller but a more continuous signal space. Speech is faster, denser, and more abstract, which is a big reason speech BCIs took longer to get right.
Neural engineering: How electrodes translate signals into words
Reading those signals is a neural engineering problem, and it’s unforgiving. Neurons are tiny, and they fire fast, so you need sensors really close to them.
In 2023, surgeons implanted Harrell’s device with four microelectrode arrays recording from 256 cortical electrodes in his speech cortex. Those arrays connect to two docking ports on top of his head that plug into a computer running the decoder.
A few engineering realities shape every design decision here:
- The closer an electrode is placed to a neuron, the cleaner the signal, but it has to deal with complicated surgery.
- More electrodes generally means richer data, which is why array density keeps climbing.
- Some newer devices skip the plug entirely and transmit wirelessly, while others sit on the brain’s surface to lower surgical risk.
There’s no free option. Every gain in signal quality tends to cost you something in surgical risk or hardware complexity.
Invasive vs. non-invasive brain-computer interfaces
The invasiveness question is the fork in the road for the whole field.
| Approach | How it is placed | Best for |
| Intracortical implant | Electrodes in brain tissue | High-accuracy speech and fine control |
| Surface / ECoG | Electrodes on the cortex | Strong signal, lower depth risk |
| EEG cap | Worn on the scalp | Research, low-stakes control, no surgery |
It has a simple rule of thumb. The closer to the neurons, the better the signal but the higher surgical risk. Harrell’s high accuracy comes from the most invasive end of that scale.
BCIs and ALS Patients: Inside the 2026 Communication Breakthrough
For ALS patients, the stakes are very high. It’s a disease that gradually takes away movement and, speech for many, while the mind stays sharp. That gap, a clear head but with no working voice, is exactly what a speech BCI targets.
Harrell is 47. He has weakness across his limbs and speech that is very hard to understand. He’s a participant in the long-running BrainGate2 clinical trial. What his data shows isn’t a one-off lab flash. It’s endurance.
Across nearly two years of home use, he logged:
- More than 183,000 sentences and close to 2 million words.
- An average of 56 wpm, which is near a conversational pace.
- And 92% of the sentences rated by him as accurate or mostly correct.
What gets me isn’t the accuracy number; it’s impressive as it is. But the detail Harrell shared through the device; being able to remind his daughter, who barely remembers his natural voice, what he used to sound like. The system uses a voice clone built from old recordings of him, so the output isn’t a generic robot tone. It’s something closer to him.
His neurosurgeon, Dr. David Brandman, said that the work suggests the field may have crossed a threshold from proof-of-concept devices toward something a person can actually use on their own terms.
Brain-Computer Interfaces as Medical Technology: From Research to Clinical Use
For years, the honest knock on BCIs was that they only worked with a research team in the room. Someone had to set up the device, recalibrate it, and babysit the software. That sounds like a science project, not a medical technology, right?
That’s why the 2026 result matters, because it breaks that limit. Harrell operates the system himself, near-daily, at home, without the researchers being beside him.
Regulation is starting to catch up too:
- In 2026, China approved a BCI for medical use outside clinical trials, a first for any country.
- In the US, these implants remain investigational devices, limited by federal law to research use.
So as a piece of medical technology, the BCI is real, but it’s still early. The engineering threshold has been crossed. The regulatory and access thresholds mostly have not, at least not yet in most of the world.
But here’s a catch. A device working reliably for one motivated person in a trial is a genuine milestone. But the threshold would be different for a hospital that will provide the implants, bill, and support. All of these are unglamorous problems that decide whether a breakthrough reaches a hundred people or a hundred thousand.
Neuroprosthetics in 2026: The Companies and Trials Scaling BCIs
Zoom out from one patient, the image gets broader, and you land in neuroprosthetics. It’s the broader effort to restore lost function, whether that’s speech, movement, or physical control for paralyzed patients. Speech is just one target. Cursor control, robotic limbs, and mobility are others.
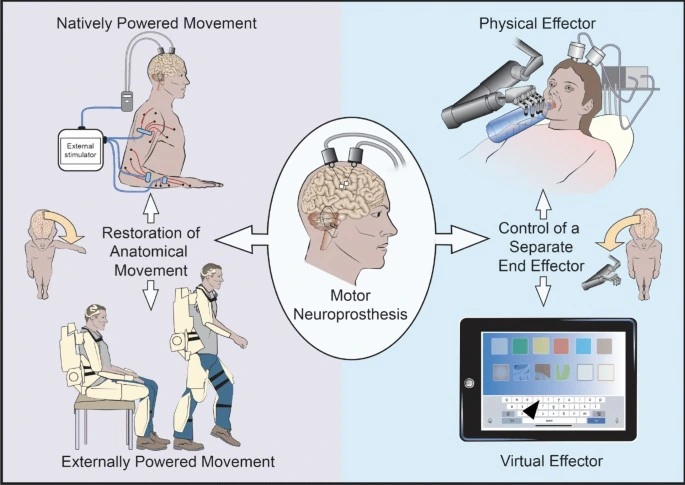
The trial numbers tell the real story. A 2024 roundup counted 67 BCI volunteers across 21 research groups from 1998 through 2023. Since then the count has roughly doubled. That’s fast for a field where every new participant needs a brain surgery.
Here’s who is actually building these:
| Player | Approach | Note |
| BrainGate | Academic, intracortical | Harrell’s speech BCI; two decades running |
| Neuralink | Fully implanted, wireless | Reported 21 implants in two years |
| Synchron | Less invasive, via blood vessels | Trials in North America and Australia |
| Precision Neuroscience | Surface electrodes | Sits on the brain, not in it |
| Neuracle | Intracortical | Behind China’s first medical approval |
What strikes me is how different the approaches are. Some teams are drilling in for maximum signal, others are threading electrodes through blood vessels to avoid open surgery. Nobody’s a winner, which usually means the field is still genuinely figuring it out.
How Brain-Computer Interfaces Enable Human-Computer Interaction
Strip away the neuroscience and a BCI is a new kind of human-computer interaction. Instead of a mouse, keyboard, or touchscreen, the input is neural activity. That reframing is useful, because it shows why this is bigger than speech alone.
Harrell doesn’t just talk through his device. He runs his computer with it. His setup pairs speech decoding for text with cursor control for navigation, plus an eye-gaze tracker he uses to fix errors before his words play aloud.
In practice, that means he can:
- Send emails and messages on his own.
- Browse the web.
- Keep up ongoing conversations with family and friends.
- Hold down a job as a climate activist, despite full paralysis.
This is the part that reframes BCIs for me. It is not only a medical fix for a lost voice. It is a working input method for a whole digital life, which is a very different and much larger idea about what human-computer interaction can be.
Limitations of Brain-Computer Interfaces and What Comes Next
I have thrown a lot of impressive numbers at you, so here is the honest counterweight. BCIs are still experimental, and it would be a mistake to read one success as a solved problem.
A few real limits:
- The evidence base is thin: Most implants so far have gone into people with spinal cord injuries, not ALS patients. We know less about how well BCIs serve ALS long-term.
- Some devices have stopped working: In certain cases where BCIs initially helped people with ALS, researchers have reported that the devices later failed, and they do not fully understand why.
- Durability is unproven: Nobody can promise how many years an implant keeps decoding cleanly.
- Access is minimal: Roughly 150 people worldwide have one. This isn’t something you can go get.
But none of that cancels the progress. It just sets the scale. The only way the open questions get answered is more trials and more volunteers like Harrell. What comes next is less than a breakthrough and more a slow accumulation of people, data, and years.
Final Thought
2026 is the year where brain-computer interfaces stopped being just a story about what might be possible and started being a story about someone’s actual Tuesday. A man is working, messaging his friends, and talking to his kid, using neurons that used to move a mouth that no longer works.
That is real, and it is early. The tech has crossed the line from lab to living room for at least one person. Whether it crosses the line to many people, affordably and reliably, is the open question. I would not bet against it, but I would not rush the timeline either.
Also read: AI Psychosis: What It Means and Why the Term Is Making Tech CEOs Uncomfortable
FAQs
Yes, in early cases at least. An ALS patient, in 2026, communicated at up to 99% word accuracy from home with a speech BCI, although the technology is still in the experimental phase and not widely available.
The top speech BCI achieved a 99% word accuracy in controlled testing using a vocabulary of 125,000 words. When used in daily life, the user found 92% of the sentences to be accurate or mostly accurate.
Mostly no. In 2026, China became the first country to approve a BCI for medical use, but in most places, including the US, these implants remain investigational and limited to clinical trials.
The brain surgery that is necessary for BCI implants is a serious risk. As the device used is more intrusive, the stronger the signal will be, but the greater the risk. There are less invasive possibilities, but they pick up on lower signals.
The 2026 speech BCI reached an average of 56 words per minute, close to natural conversational speed. That is a large jump over older brain-typing systems that ran far slower.
Not proven. Some implants have run reliably for almost two years, but others have stopped working over time for unclear reasons. Long-term durability is one of the field’s biggest open questions.
